Last updated: September 2026
Is it harmful to take sleeping pills regularly? It depends on the drug and on you — but no major guideline endorses long-term nightly use. The FDA cleared these medicines for short-term use, and clinicians are told to reassess rather than refill indefinitely.
Key takeaways
- The FDA has approved sleep medication for short-term use (4 to 5 weeks), and advises that insomnia which has not resolved within 7 to 10 days be evaluated further (ACP 2016).
- In April 2019 the FDA added a boxed warning — its strongest — to eszopiclone, zaleplon and zolpidem for complex sleep behaviours that have caused serious injuries and deaths (FDA).
- The American College of Physicians rates CBT-I as first-line treatment (strong recommendation, moderate-quality evidence) and adding medication only as a weak recommendation on low-quality evidence.
- Every single drug recommendation in the American Academy of Sleep Medicine’s 2017 guideline is graded WEAK — including the ones telling clinicians to use these medicines.
- Observational studies link hypnotics to dementia, serious injury and fractures, but that study design cannot separate the drug from the reason it was prescribed.
- The widely repeated cancer figure traces to one 2012 matched cohort study; it reports an association, not a demonstrated cause.
What counts as a sleeping pill?
“Sleeping pill” covers several drug families that work differently, and the risk picture is not the same across them. The prescription group most people mean is the non-benzodiazepine hypnotics — eszopiclone, zaleplon and zolpidem, often called Z-drugs — which the FDA describes as working by slowing activity in the brain.
Alongside them sit the older benzodiazepines, the melatonin-receptor agonist ramelteon, the low-dose antidepressant doxepin, and the newer orexin-receptor antagonists such as suvorexant. Over-the-counter products are a separate category again, and a separate question from the prescription drugs that treating a sleep disorder usually involves.
| Drug family | Examples | What the AASM 2017 guideline does |
|---|---|---|
| Non-benzodiazepine hypnotics | Eszopiclone, zaleplon, zolpidem | Suggests use for specific insomnia patterns — all WEAK |
| Orexin-receptor antagonists | Suvorexant | Suggests use for sleep maintenance — WEAK |
| Melatonin-receptor agonists | Ramelteon | Reviewed; measured sleep gains fell below clinical significance |
| Over-the-counter and supplements | L-tryptophan, valerian, melatonin | Suggests clinicians not use them for insomnia — WEAK |
Is it harmful to take sleeping pills regularly?
The honest answer is that nobody has the trial evidence to say cleanly, and that gap is itself the finding. The ACP guideline states plainly that evidence “is insufficient to evaluate the balance of the benefits and harms of long-term use of pharmacologic treatments in adults with chronic insomnia disorder.”

That is not the same as “safe.” It means the studies regulators relied on were short, and regular long-term use sits outside what was tested. The FDA’s own framing matches: approval was for short-term use, with a prompt to re-evaluate anyone still not sleeping after a week to ten days. Regular indefinite use is not the tested scenario — it is what happens when the tested scenario runs on.
4 risks that show up when you take sleeping pills regularly
Complex sleep behaviours. The FDA has received reports of people taking these medicines and “accidentally overdosing, falling, being burned, shooting themselves, and wandering outside in extremely cold weather.” These can occur after a first dose or after continued use, at ordinary doses, and people often do not remember them (FDA consumer update).
Next-day impairment. ACP notes that FDA labels warn of daytime impairment, sleep driving, behavioural abnormalities and worsening depression. This is the risk most likely to touch an ordinary working day, and it is part of why you can feel tired despite a full night in bed.
Falls and fractures, especially with age. Observational data reviewed by ACP associate hypnotics with dementia, serious injury and fractures. The FDA recommends lower doses in women and in older or debilitated adults — a dosing decision that already reflects how sleep and sensitivity change with age.
The drug is no longer a variable you can test. Once a medicine is nightly and indefinite, there is no clean baseline left to compare against, which makes the underlying cause of the insomnia harder to see.
What do the guidelines say about taking sleeping pills regularly?
Two major guidelines converge, and both put behaviour ahead of pharmacology. The ACP recommends that all adult patients receive cognitive behavioural therapy for insomnia as the initial treatment for chronic insomnia disorder — a strong recommendation on moderate-quality evidence. Medication enters only through a second, weaker recommendation: a shared decision about short-term use, if CBT-I alone has not worked.
The AASM 2017 guideline is about drug selection, and it is candid about its own footing. Under GRADE, it explains, a weak recommendation “reflects a lower degree of certainty in the outcome and appropriateness of the patient-care strategy for all patients.” Every drug recommendation in that guideline carries that label. The task force attributes the downgrade to industry funding of most trials, the small number of eligible trials per drug, and heterogeneity in the data.
Worth sitting with: the strongest recommendation in this entire literature is for a talking therapy, not a tablet. If you are working through what is causing the insomnia in the first place, that ordering is the practical takeaway.
Does the cancer claim hold up?
This one deserves its own section, because it circulates widely and usually without its caveats. The source is a 2012 matched cohort study by Kripke and colleagues in BMJ Open, which followed 10,529 patients prescribed hypnotics against 23,676 matched controls for an average of 2.5 years. It reported a 35% higher cancer incidence among users, and an adjusted hazard ratio for death of 4.56 (95% CI 3.95 to 5.26).
Those numbers are real and the paper is published. What they are not is proof of cause. The authors describe controlling for age, sex, ethnicity, marital status, BMI, alcohol and smoking, and stratifying on up to 116 comorbidity combinations specifically “to minimise confounding by indication” (full text). That they had to work that hard is the point: people prescribed sleeping pills differ from people who are not, in ways a cohort design can reduce but cannot remove.
So the accurate sentence is narrow. One large observational study found an association between hypnotic prescriptions and both cancer and mortality. A reader deciding what to do tonight should treat that as a reason to ask a clinician a question, not as a settled fact about their own medicine.
What does this evidence not cover?
It does not cover people taking these drugs for years, because the trials were short. It does not tell you how the risk splits across the drug families, since ACP found insufficient evidence on comparative safety between them. And it says nothing about stopping — the guidelines cover starting and choosing, not tapering, which is a conversation for the prescriber who knows the history.
It also does not address the sleep problems that are not insomnia at all. Untreated sleep apnoea produces broken nights that a sedative does not address, and the stages of sleep are affected differently by different drugs. Anyone who snores heavily and wakes unrefreshed is asking a different question from the one this article answers.
Frequently asked questions
Is it harmful to take sleeping pills regularly for years?
No guideline supports it, and the trial evidence does not extend that far. The ACP states that evidence is insufficient to weigh the benefits and harms of long-term use. FDA approval covers short-term use of 4 to 5 weeks. Years of nightly use sits outside what was studied, which is a reason to review it with a prescriber rather than assume it is fine.
Are over-the-counter sleep aids safer than prescription ones?
Not automatically, and the AASM guideline does not treat them as a gentler alternative. It suggests clinicians not use L-tryptophan or valerian for insomnia, and reviewed melatonin and diphenhydramine in the same over-the-counter section. “Available without a prescription” describes how you buy something, not how well it works or how it interacts with your other medicines.
What is CBT-I, and why do guidelines rank it first?
Cognitive behavioural therapy for insomnia combines cognitive work on sleep, behavioural steps such as sleep restriction and stimulus control, and education. ACP grades it a strong recommendation on moderate-quality evidence and notes any harms are likely mild. It can be delivered in person, by phone, through web modules or self-help books — not only in a clinic.
Can I just stop taking them if I have been taking them nightly?
That is a question for your prescriber, not an article. The published guidelines address choosing and starting medication rather than discontinuing it, so there is no consensus protocol here to hand you. What the evidence does support is not making that decision alone after months or years of nightly use.
Do sleeping pills actually add much sleep?
Less than most people expect, and the size varies by drug. In the AASM review of ramelteon, pooled objective total sleep time rose by 6.58 minutes (CI +1.36 to +11.80), which the task force judged below the threshold for clinical significance. That is one drug, but it illustrates why these recommendations are graded weak rather than strong.
Does a better sleep environment replace medication?
No, and it should not be framed that way. Sleep hygiene is one component of CBT-I, which guidelines rank first — but CBT-I is a structured programme, not a new mattress. Comfort measures are worth getting right on their own terms, and they can be explored alongside natural approaches to insomnia and a clinician’s advice.
Where sleep comfort fits in this picture
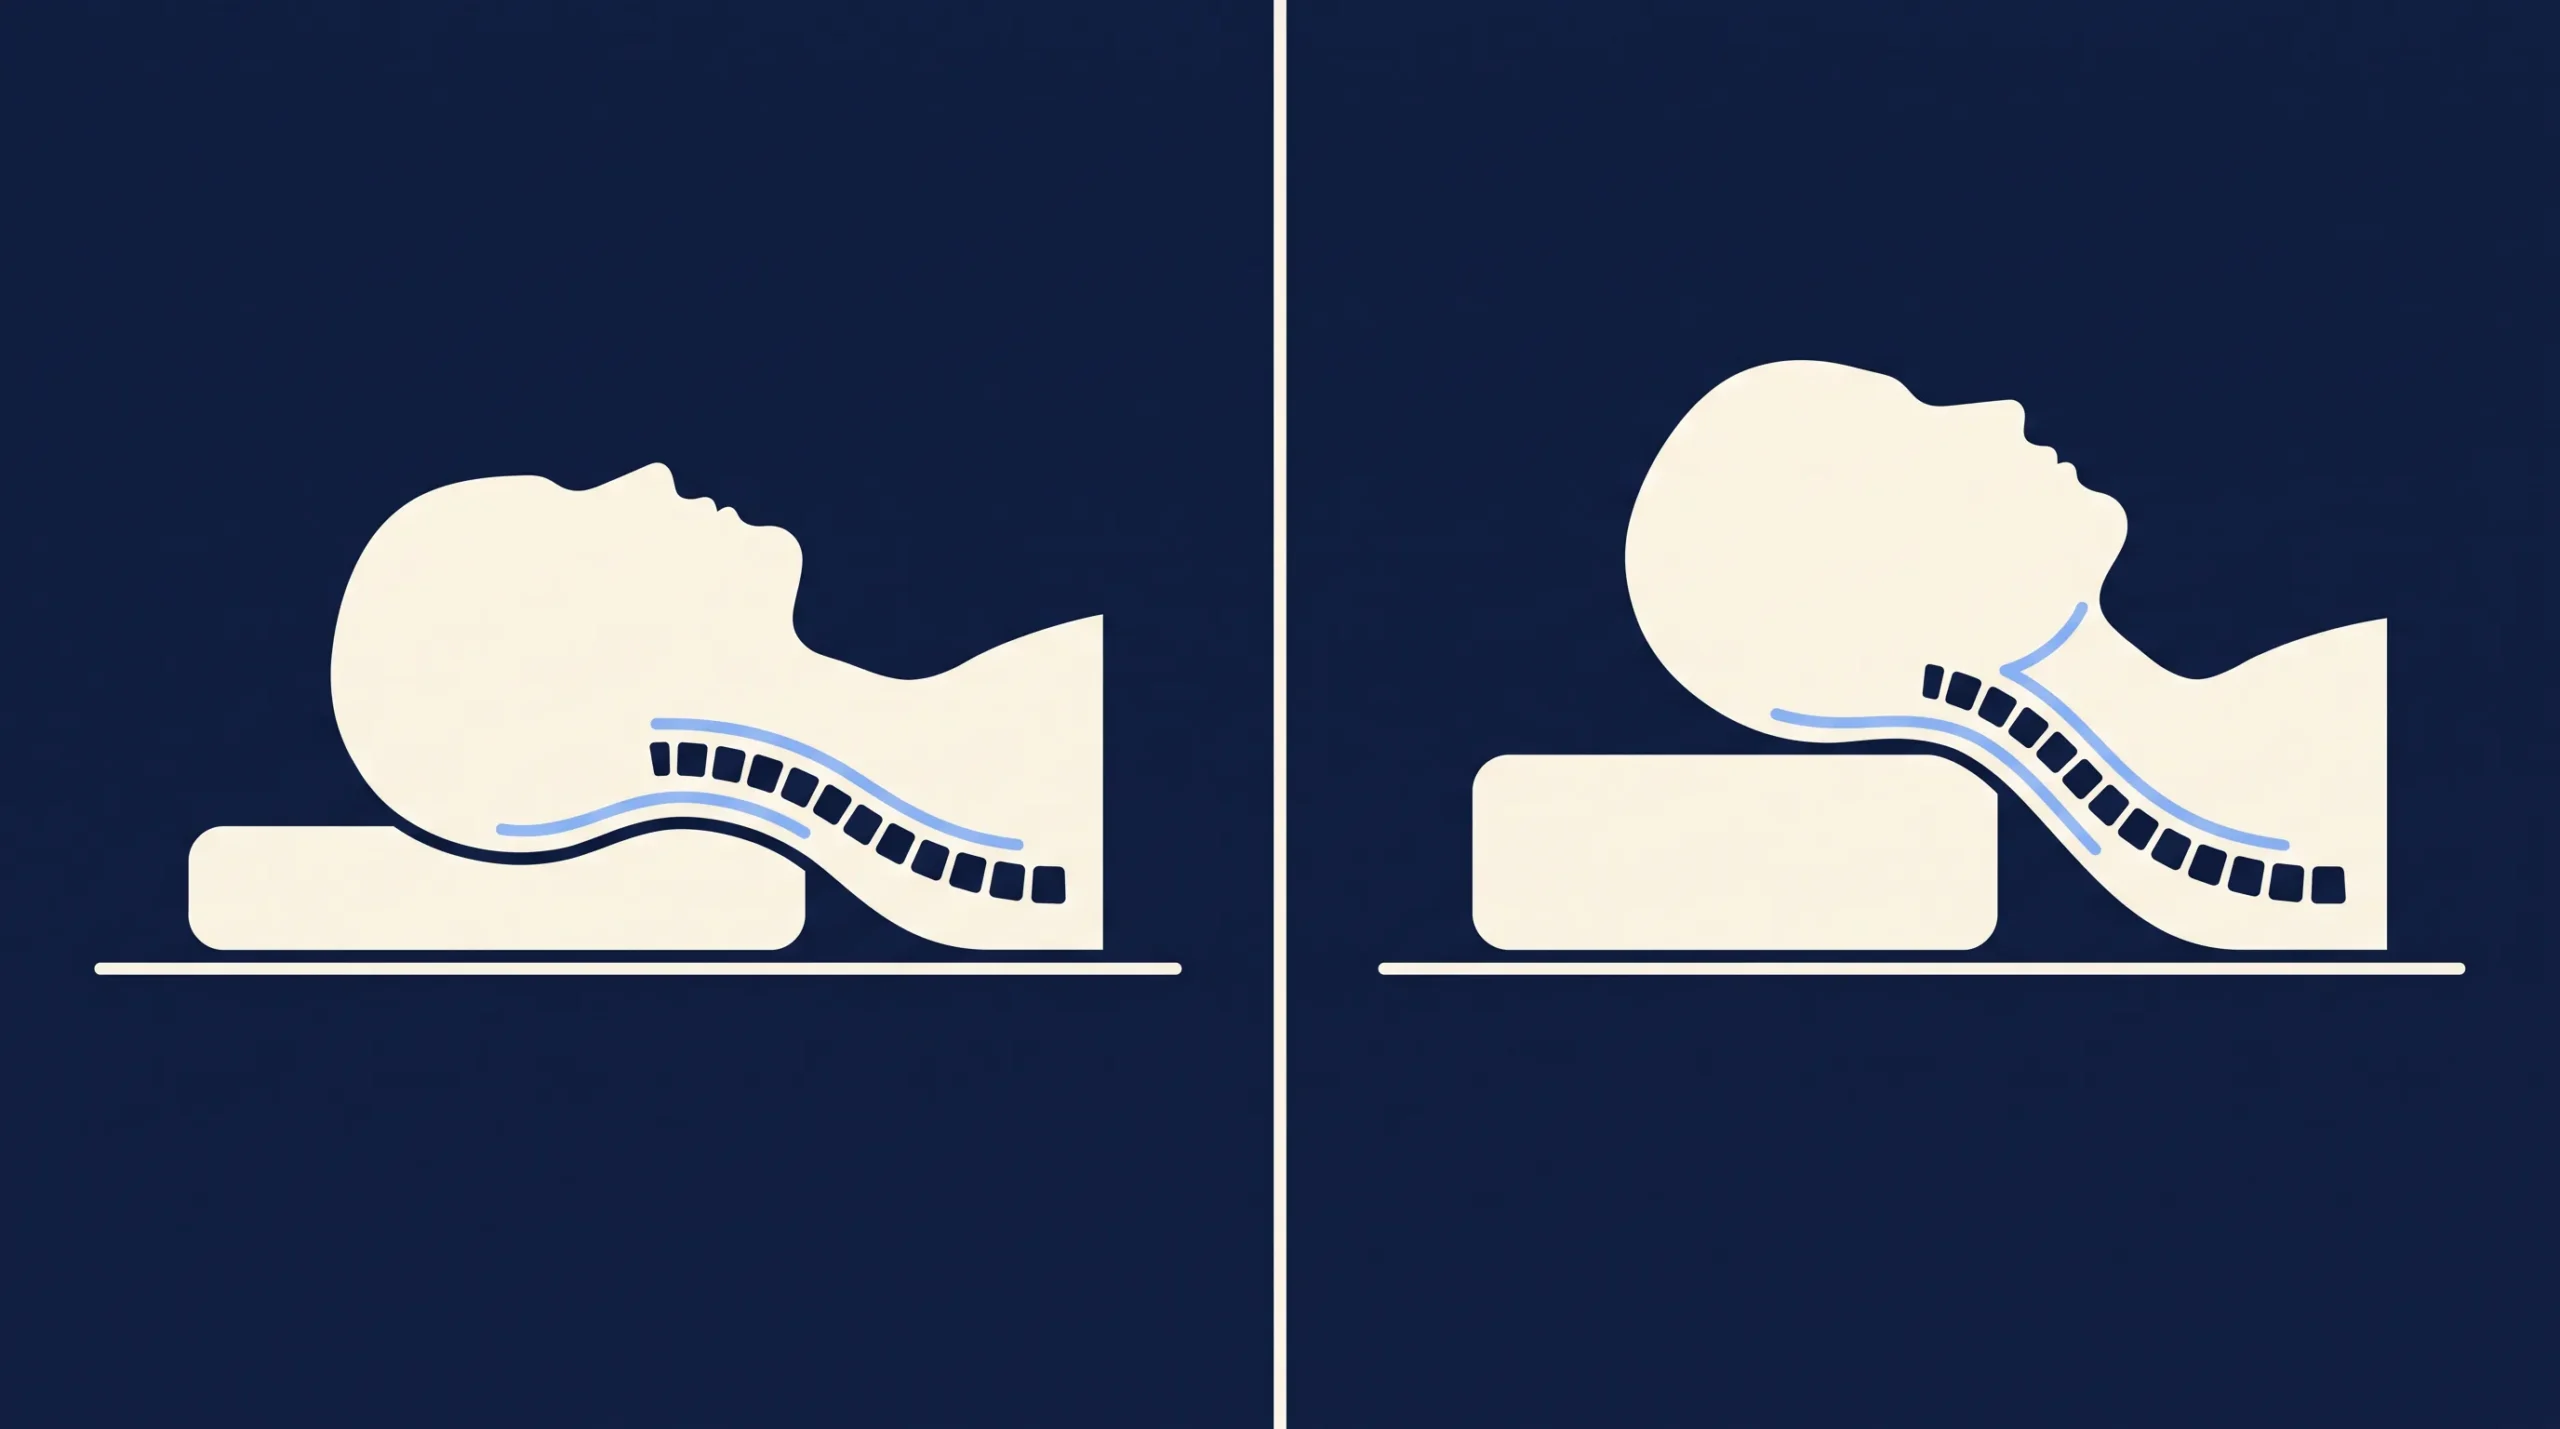
Nothing above is a reason to change a prescription — that decision belongs to you and your prescriber, and this article exists to help you arrive at that conversation better informed. What the guidelines do place ahead of medication is CBT-I, and sleep hygiene is one strand of it. Our practical guide to better sleep covers that ground, and if neck or shoulder discomfort is one of the things waking you, matching pillow loft to your sleeping position is the cheapest variable in the room to adjust.
Methodology: pillow dimensions come from the makers’ production specifications, and every clinical figure above is drawn from the guidelines and studies linked in the text. Where the older version of this article stated a risk we could not trace to a primary source, we removed it rather than soften it. If you are unsure which loft suits you, our notes on the best pillow for side sleepers and the best firm pillow set out the trade-offs, and the Aeris Contour Pillow is the shape we point side and back sleepers toward first.
Advertisement

FirmNest Extra Firm Pillow
64 × 40 × 14 cm, 1.5 kg extra-firm memory-foam core.
See the FirmNest Extra Firm Pillow on AmazonProducts mentioned in this guide
 Aeris Contour Pillow — 60 × 40 cm, memory foam, 12 cm and 10 cm contour lobes
 FirmNest Extra Firm Contour Pillow — 60 × 40 cm, same 12/10 cm lobes in a denser core